1. Executive Summary & Clinical Diagnostic Context #
Antinuclear antibody (ANA) testing represents the foundational serological screen for systemic autoimmune rheumatic diseases (SARD), including Systemic Lupus Erythematosus (SLE), Systemic Sclerosis (SSc), Sjögren's Syndrome (SjS), Mixed Connective Tissue Disease (MCTD), and Idiopathic Inflammatory Myopathies (IIM). For over six decades, the Indirect Immunofluorescence Assay (IFA) utilizing human epithelial-2 (HEp-2) substrate has been revered as the definitive diagnostic gold standard.
Autoimmune Serology Note — Dr. S Paul, Chief Scientific Reviewer: "Never sign out a negative solid-phase ANA multiplex screen on a patient with suspected systemic sclerosis without running a reflex HEp-2 IFA slide at 1:80 dilution. Solid-phase beads routinely lack native nucleolar RNA polymerase III and centromere conformational epitopes."
However, the rapid escalation of laboratory test volumes, escalating labor costs, subjective inter-observer variability, and the demand for high-throughput laboratory automation have driven clinical diagnostic laboratories toward solid-phase assays—primarily Enzyme-Linked Immunosorbent Assays (ELISA), Chemiluminescent Immunoassays (CLIA), and Multiplex Bead Assays (MBA / Luminex technology).
While solid-phase platforms offer walk-away automation, quantitative output, and eliminate fluorescence microscopy, they present substantial diagnostic hazards. Specifically, solid-phase panels can yield catastrophic false-negative results for autoantibodies against non-coated cellular antigens (e.g., anti-Ro52/SSA, anti-dense fine speckled 70 [DFS70], anti-ribosomal P, and rare nucleolar antigens). Conversely, ultra-sensitive bead arrays detect low-avidity, clinically irrelevant autoantibodies, producing high rates of false-positive results in healthy elderly populations.
This technical manual provides a comprehensive, bench-level comparison of HEp-2 IFA versus solid-phase multiplex immunoassays. It details the international consensus on ANA patterns (ICAP), optical filter physics, dilution threshold thermodynamics, automated digital imaging validation, and hybrid diagnostic screening algorithms compliant with ACR, EULAR, and ISO 15189:2022 laboratory accreditation standards.
2. Theoretical Foundations and Optical Physics of HEp-2 IFA #
2.1 The HEp-2 Cell Substrate Architecture #
HEp-2 cells are derived from human laryngeal carcinoma cells (contaminated historically with HeLa cells). Their utility as an autoimmune substrate stems from:
- Human Origin: Unlike rodent kidney or liver sections used in the 1960s, human cells express native, correctly folded human nuclear and cytoplasmic epitopes without cross-species antigen mismatches.
- Prominent Nuclei and Abundant Cytoplasm: HEp-2 cells exhibit massive nuclear-to-cytoplasmic volume ratios, allowing clear visualization of fine nucleoplasmic, nucleolar, centromeric, and nuclear envelope architectures.
- Mitotic Cells in All Phases: In a properly cultured HEp-2 monolayer, 1 - 3% of cells are actively undergoing mitosis (prophase, metaphase, anaphase, telophase). Mitotic chromatin staining is mandatory to distinguish true clinically significant patterns (such as homogeneous chromatin versus speckled non-chromatin autoantibodies).
HEp-2 IFA Optical Path:
[LED / Mercury Arc Lamp (488 nm)] ──► Excitation Filter (470-490 nm)
                                                   │
                                                   ▼
[HEp-2 Substrate + Patient Serum + Anti-Human IgG FITC]
                                                   │
                                                   ▼
                                        Dichroic Mirror (505 nm)
                                                   │
                                                   ▼
                                      Barrier / Emission Filter (515-545 nm)
                                                   │
                                                   ▼
                                  [Green Fluorescent Signal (520 nm)]
2.2 The Physics of FITC Fluorescence in Microscopy #
Indirect immunofluorescence relies on Fluorescein Isothiocyanate (FITC) conjugated to affinity-purified goat anti-human IgG (Fc or H+L chain specific):
- Excitation Peak: 495 ext{ nm} (blue spectrum).
- Emission Peak: 519 ext{ nm} (green spectrum).
- Stokes Shift: 24 ext{ nm}.
To prevent autofluorescence and optical bleed-through, microscopes must be configured with hard-coated narrow-bandpass interference filters (Excitation: 470/40 ext{ nm}, Dichroic: 505 ext{ nm LP}, Emission: 535/30 ext{ nm}). Light source intensity must be routinely validated using fluorescent calibration beads; mercury-vapor burner degradation (>200 ext{ hours} operational time) drops excitation energy by >40%, artificially depressing endpoint titers from 1:640 down to 1:160. Modern diagnostic facilities must mandate stabilized high-power LED light sources (470 ext{ nm}) with continuous electronic feedback illumination.
3. Solid-Phase Immunoassay Architectures (ELISA vs. Multiplex Beads) #
In contrast to the whole-cell morphological landscape of HEp-2 cells, solid-phase immunoassays rely on immobilized, purified natural or recombinant antigens.
Comparison of Substrate Architectures:

1. HEp-2 Cell (IFA):
   ┌───────────────────────────────────────────────┐
   │ >150 native human autoantigens               │
   │ Intact quaternary complexes, RNA-protein core │
   │ True morphological localization               │
   └───────────────────────────────────────────────┘

2. Multiplex Bead Array (MBA):
   ┌────────────┐   ┌────────────┐   ┌────────────┐
   │ Bead 1:    │   │ Bead 2:    │   │ Bead 3:    │
   │ Ro60 (Rec) │   │ La/SSB     │   │ Scl-70     │
   └────────────┘   └────────────┘   └────────────┘
   * Restricted strictly to pre-selected coated antigens.
3.1 Enzyme-Linked Immunosorbent Assay (Solid-Phase Screening ELISA) #
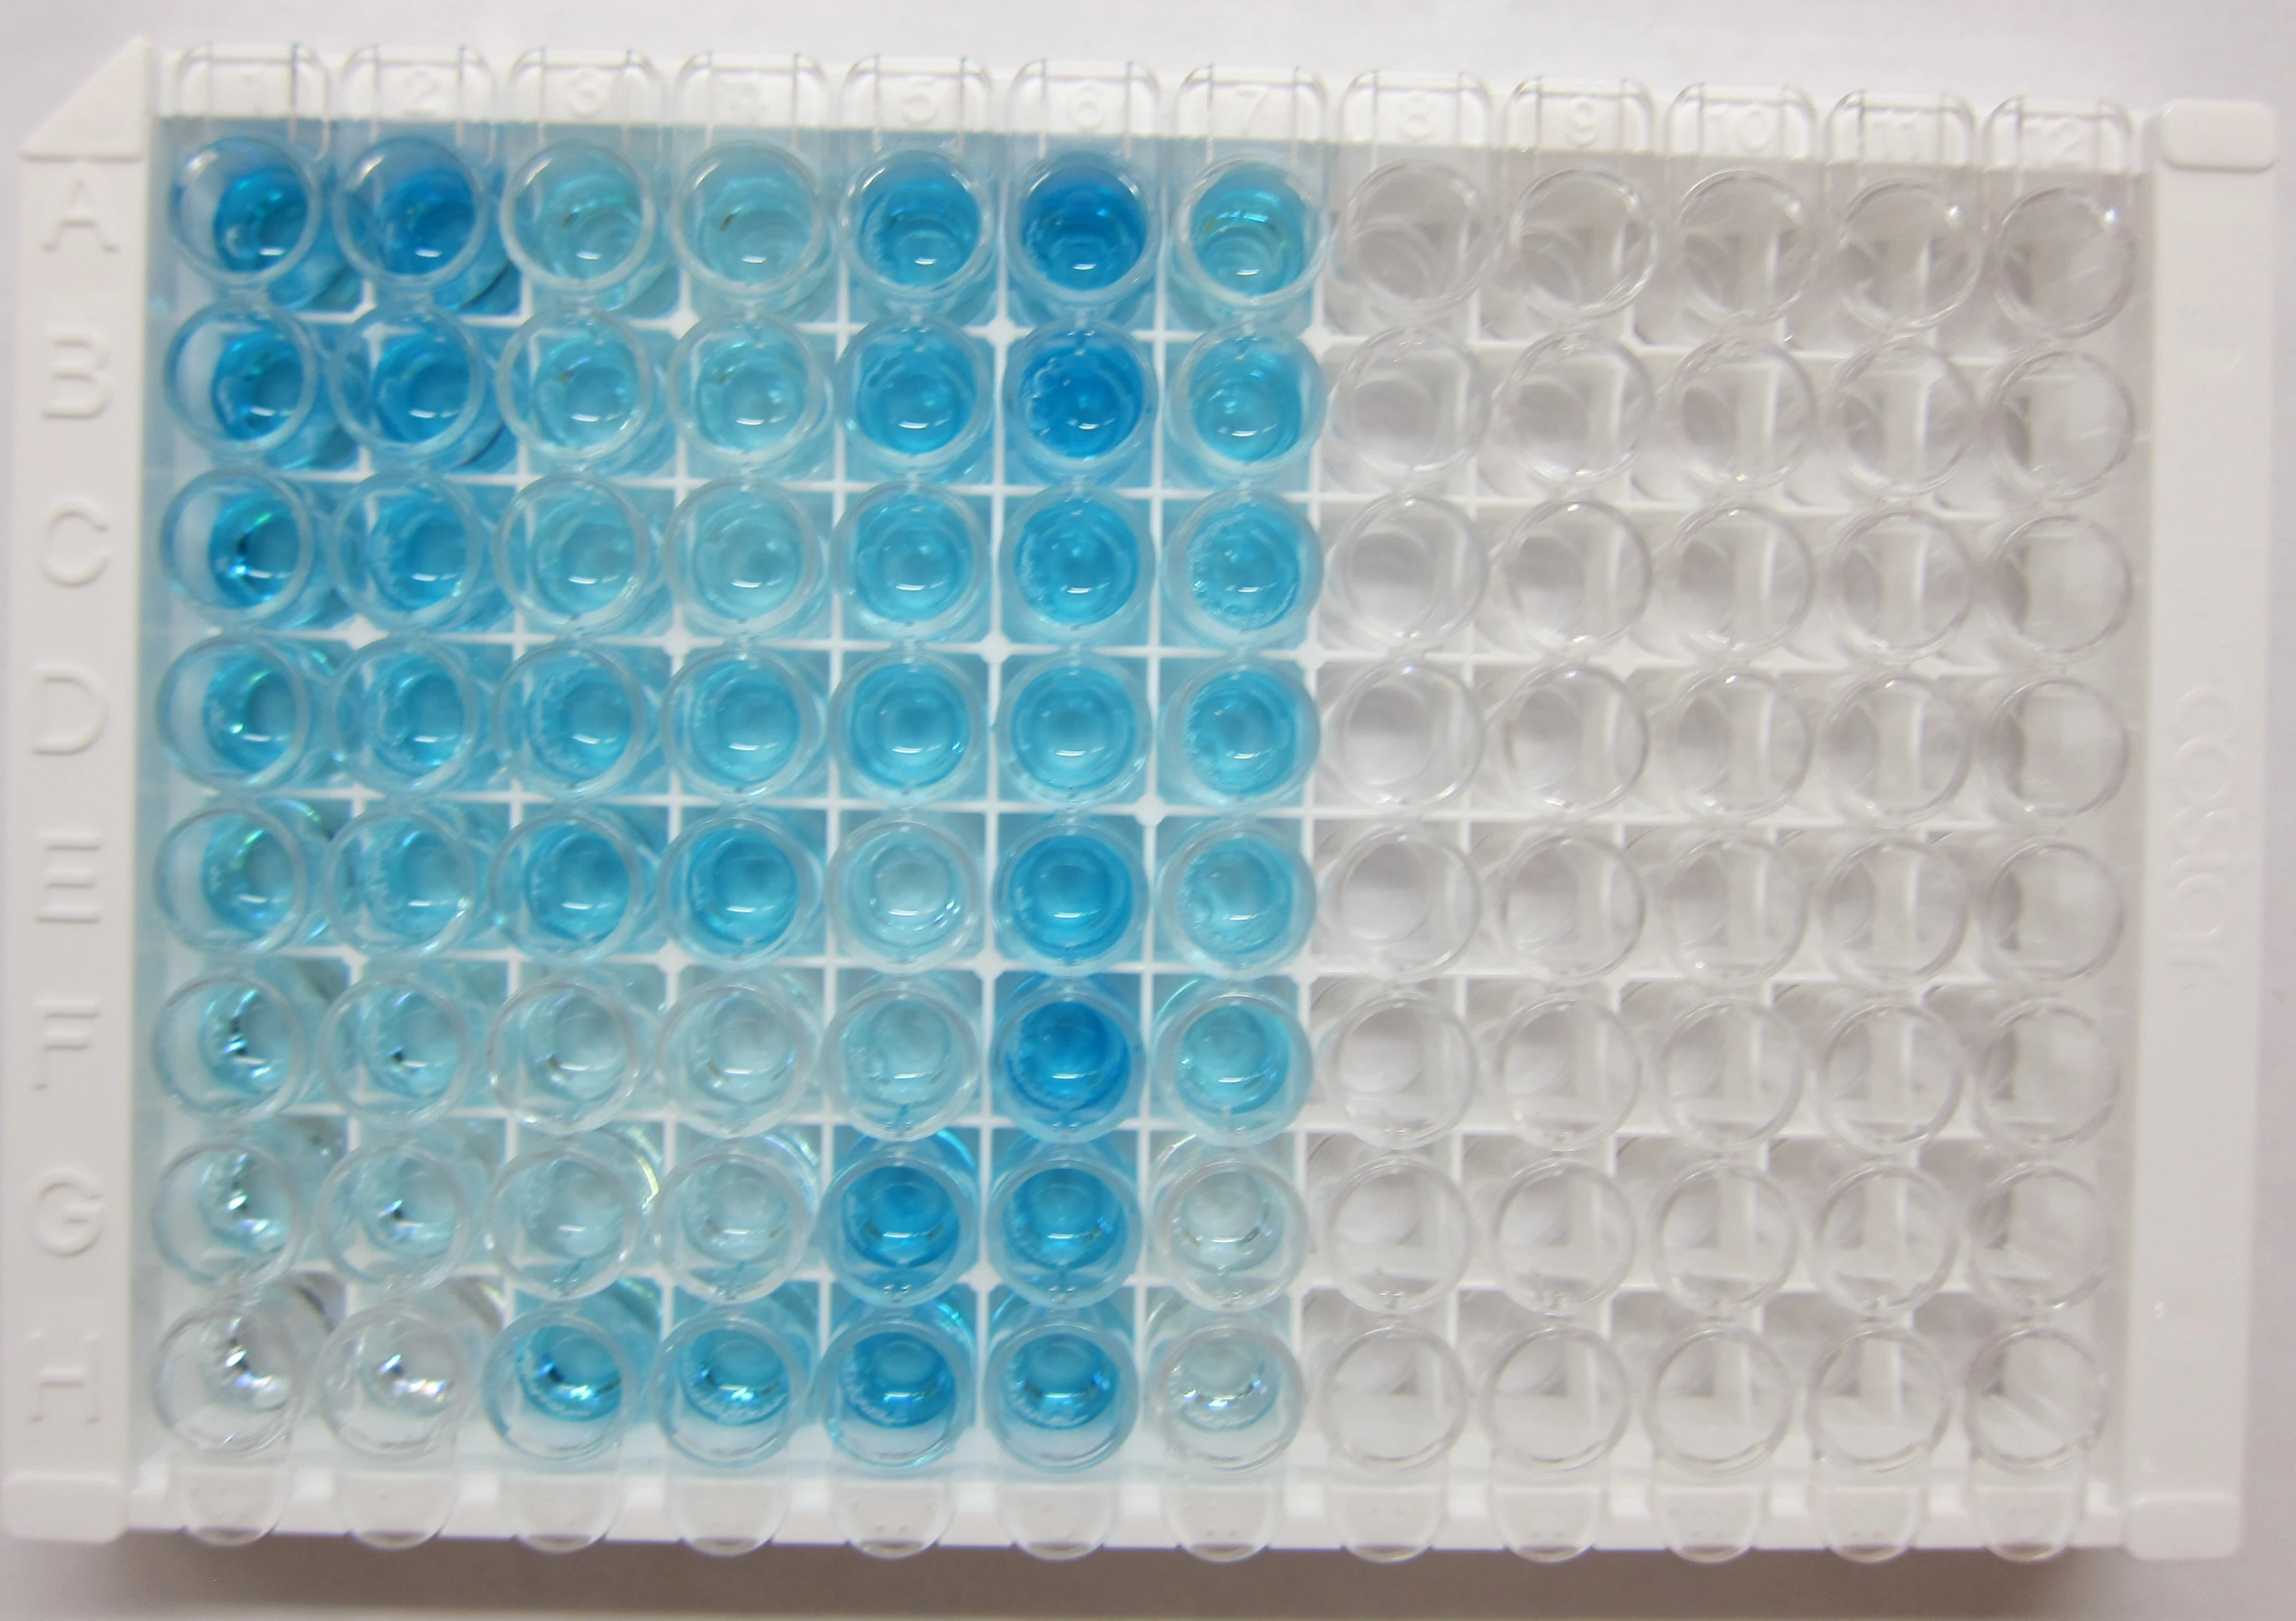
Screening ELISAs utilize 96-well microplates coated with a mixture of purified nuclear antigens (typically a cocktail of SSA/Ro60, Ro52, SSB/La, Sm, Sm/RNP, Scl-70, Jo-1, Centromere B, and native dsDNA).
- Advantage: Rapid automated processing on open clinical chemistry analyzers; qualitative index value output (positive/negative ratio).
- Critical Failure Mode: Stoichiometric imbalance. In a mixed-antigen well, high-molecular-weight antigens out-adsorb smaller proteins. If a patient possesses high-titer anti-Jo-1 but low-affinity antibodies, the limited coating density of Jo-1 in a mixed well can produce a false-negative screen.
3.2 Multiplex Bead Arrays (MBA / Flow Cytometry Bead Technology) #
Multiplex systems (e.g., Luminex xMAP) employ internally dyed polystyrene or magnetic microspheres. Distinct spectral ratios of red and infrared dyes yield up to 500 uniquely identifiable bead sets.
- Each bead set is covalently coupled (via carbodiimide chemistry) to an isolated recombinant autoantigen.
- After incubation with diluted patient serum (1:100), bound IgG is labeled with Phycoerythrin (PE)-conjugated anti-human IgG.
- High-speed fluidics hydrodynamically focus the beads past two lasers:
- Classification Laser (635 ext{ nm}): Identifies the bead identity (which antigen is being measured).
- Reporter Laser (532 ext{ nm}): Quantifies fluorescent emission from bound PE (determines antibody quantity).
ELISA vs. IFA: Key Differences in Clinical Autoantibody Testing #
The debate between ELISA (Enzyme-Linked Immunosorbent Assay) and IFA (Indirect Immunofluorescence Assay) represents a fundamental decision in clinical immunology and diagnostic laboratory operations. While both methodologies detect circulating antinuclear antibodies, their analytical architectures serve divergent diagnostic objectives:
Comprehensive Comparison: ELISA vs. HEp-2 IFA #
| Parameter | Solid-Phase Screening ELISA | HEp-2 Indirect Immunofluorescence (IFA) |
|---|---|---|
| Substrate Architecture | Purified recombinant or native antigen cocktail coated on polystyrene wells | Preserved monolayer of human epithelial cells (HEp-2) in active mitotic cycle |
| Antigen Coverage | Restricted to predefined antigens (typically 6 to 11: Ro, La, Sm, RNP, Scl-70, Jo-1, dsDNA) | Comprehensive native display (> 100 nuclear, nucleolar, and cytoplasmic antigens) |
| Clinical Gold Standard | Rapid high-throughput screen; high negative predictive value | ACR / CLSI Gold Standard for diagnostic systemic autoimmune rheumatic disease |
| Output Metric | Semiquantitative Antibody Index (Ratio of Optical Density to cut-off calibrator) | Serial end-point titer (1:80, 1:160, 1:320, 1:640+) and ICAP morphological pattern |
| Throughput & Automation | High-throughput fully automated random-access analyzers (> 120 ext{ tests/hour}) | Semi-automated slide processing; requires expert manual or automated fluorescence imaging |
| Inter-Observer Variability | Low (CV < 5.0% photometer OD readout) | Moderate (15.0% - 25.0% CV subjective pattern interpretation) |
| False-Negative Risk | Fails to detect antibodies against rare autoantigens omitted from the cocktail | Rare; highly sensitive to diverse nuclear and cytoplasmic antigen architectures |
4. Head-to-Head Comparative Analytical Matrix #
The following matrix compares clinical, operational, and analytical parameters between HEp-2 IFA and Multiplex Bead Assays.
| Analytical Parameter | HEp-2 Cell IFA (Gold Standard) | Multiplex Bead Array (MBA) | Solid-Phase Screening ELISA |
|---|---|---|---|
| Antigen Coverage | Complete Proteome (>150 cellular antigens) | Restricted (8 - 15 predefined antigens) | Restricted (8 - 12 pooled antigens) |
| Native Epitope Presentation | Preserved native tertiary/quaternary structures | Variable; recombinant proteins may lack human PTMs | Often denatured by passive polystyrene binding |
| Turnaround Time (96 tests) | 3.0 - 4.5 ext{ hours} (manual slide handling) | 1.5 - 2.0 ext{ hours} (fully automated walk-away) | 2.0 - 2.5 ext{ hours} |
| Analytical Output | Semi-quantitative titer (1:80, 1:160, dots) + Pattern | Quantitative antibody concentration (ext{U/mL} or ext{IU/mL}) | Qualitative Optical Density (OD) Ratio |
| Inter-Operator Reproducibility | Moderate (CV: 25% - 45% visual subjectivity) | High (CV: <8% instrument-read precision) | Good (CV: 8% - 14%) |
| Sensitivity for SLE | >95% | 85% - 90% (misses rare/uncoated lupus antigens) | 88% - 92% |
| Sensitivity for SSc & Myositis | >90% | Poor (<65% due to missing nucleolar antigens) | Moderate (60% - 70%) |
| Specific DFS70 Differentiation | Yes (ICAP AC-2 pattern easily confirmed) | Only if specific anti-DFS70 bead is included | No (generates false-positive ANA screen) |
| Capital Equipment Cost | <span class="inline-math font-serif italic text-current font-semibold px-0.5">15,000 (Fluorescence Scope) to 80,000 (Automated Imager) | <span class="inline-math font-serif italic text-current font-semibold px-0.5">60,000 – 140,000 (Multiplex Flow Analyzer) | <span class="inline-math font-serif italic text-current font-semibold px-0.5">10,000 – 35,000 (Standard Plate Reader) |
5. The International Consensus on ANA Patterns (ICAP) Reference Guide #
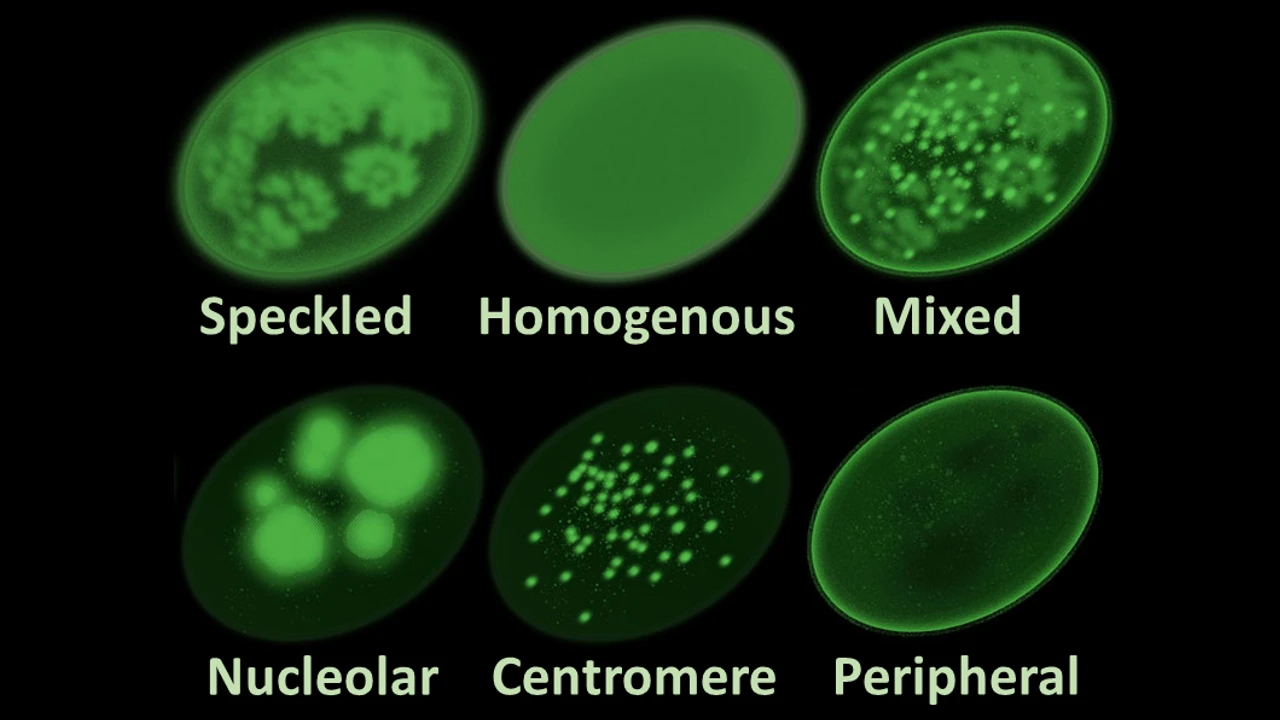
The International Consensus on ANA Patterns (ICAP) categorizes HEp-2 patterns into discrete Alpha-Numeric (AC) codes. Recognizing these patterns is paramount because solid-phase bead assays cannot report morphological distribution.
ICAP Major Branching Tree:
                       HEp-2 IFA Staining
                               │
       ┌───────────────────────┴───────────────────────┐
       ▼                                               ▼
Nuclear Patterns (AC-1 to AC-14)             Cytoplasmic Patterns (AC-15 to AC-23)
       │                                               │
  ┌────┴────┐                                     ┌────┴────┐
  ▼         ▼                                     ▼         ▼
Homogeneous Speckled                           Fibrillar  Mitochondrial
 (AC-1)   (AC-2 to AC-5)                        (AC-15)    (AC-21, AMA)
5.1 Nuclear Homogeneous Pattern (AC-1) #
- Cellular Morphology: Diffuse, uniform staining of the entire interphase nucleus; chromatin of mitotic cells (metaphase plate) is intensely and cleanly stained.
- Underlying Autoantigens: Native double-stranded DNA (dsDNA), histones (H1, H2A, H2B, H3, H4), and nucleosomes.
- Clinical Association: Pathognomonic for Systemic Lupus Erythematosus (SLE) and Drug-Induced Lupus (DIL).
5.2 Dense Fine Speckled Pattern (AC-2) #
- Cellular Morphology: Heterogeneous, dense fine speckles distributed throughout the interphase nucleoplasm; metaphase plates exhibit intensely stained, speckled chromatin.
- Underlying Autoantigen: DFS70 / LEDGF (Lens Epithelium-Derived Growth Factor).
- Crucial Diagnostic Pitfall: This is the most common false-positive ANA pattern in healthy individuals (>10% of normal healthy donors). If AC-2 is present at high titers in an asymptomatic patient without SARD symptoms, autoimmune disease is exceptionally unlikely. Solid-phase ELISA panels lacking DFS70 antigen misclassify these healthy patients as "ANA Positive", causing unnecessary psychological distress and clinical workups.
5.3 Fine Speckled Pattern (AC-4) #
- Cellular Morphology: Fine speckles throughout the nucleus; mitotic chromosomes are distinctly negative (dark chromosomal area in metaphase).
- Underlying Autoantigens: SS-A/Ro (Ro60), SS-B/La, Mi-2.
- Clinical Association: Primary Sjögren's Syndrome, neonatal lupus, subacute cutaneous lupus erythematosus (SCLE).
5.4 Centromere Pattern (AC-3) #
- Cellular Morphology: Distinct discrete uniform speckles (46 - 92 dots per nucleus corresponding to kinetochores); aligned centrally at the equatorial plate during metaphase.
- Underlying Autoantigen: CENP-A, CENP-B, CENP-C.
- Clinical Association: Highly specific for Limited Cutaneous Systemic Sclerosis (lcSSc / CREST syndrome).
5.5 Nucleolar Patterns (AC-8, AC-9, AC-10) #
- Cellular Morphology: Homogeneous, clumpy, or punctate staining confined entirely to the nucleoli within interphase nuclei.
- Underlying Autoantigens: PM-Scl, Th/To, RNA Polymerase I, Fibrillarin (U3-RNP).
- Clinical Association: Systemic Sclerosis, Scleroderma-Myositis overlap syndrome. Multiplex bead arrays routinely fail to detect these autoantibodies because rare nucleolar proteins are rarely coated on commercial beads.
6. Benchtop Protocol: Standardized HEp-2 IFA Testing (ISO 15189 Compliant) #
This standard operating procedure guarantees diagnostic reproducibility across clinical laboratory runs.
6.1 Reagent and Instrument Setup #
- Substrate Slides: Pre-fixed HEp-2 cell slides stored at -20° ext{C} or 2° ext{C} - 8° ext{C}. Equilibrate foil pouches to room temperature for 30 minutes before opening to prevent water condensation on the monolayer.
- Sample Diluent / Wash Buffer: 10 ext{ mM} Phosphate-Buffered Saline (PBS), pH 7.4 ± 0.2 (137 ext{ mM NaCl}, 2.7 ext{ mM KCl}, 10 ext{ mM Na}2 ext{HPO}4, 1.8 ext{ mM KH}2 ext{PO}4).
- Conjugate: FITC-labeled goat anti-human IgG (heavy-chain gamma-specific), containing Evans Blue counterplate dye (stains cytoplasm deep red to contrast green nuclear signals).
- Mounting Medium: Anti-fade mounting medium (90% glycerol in carbonate buffer, pH 9.0, containing 2.5% ext{ w/v} DABCO [1,4-diazabicyclo[2.2.2]octane]).
6.2 Step-by-Step Procedure #
- Serum Dilution Screening Threshold:
- Dilute patient serum specimens 1:80 or 1:160 in PBS.
- Clinical Standard: The American College of Rheumatology (ACR) recommends 1:160 for adult screening to optimize clinical specificity (>95%), while 1:80 provides higher sensitivity (>98%) but elevated false-positive rates in benign controls.
- Slide Inoculation:
- Place HEp-2 slides into a humidified incubation chamber.
- Dispense exactly 30 ext{ }mu ext{L} of diluted patient serum onto designated wells. Avoid touching the cell substrate with pipette tips.
- Run three mandatory controls on every slide run:
- Negative Control: Validated healthy human serum (<1:40).
- Positive Homogeneous Control (AC-1): Titered lupus serum.
- Positive Speckled Control (AC-4): Titered Sjögren's serum.
- Primary Incubation:
- Close humidified chamber to prevent evaporation. Incubate at 22° ext{C} ± 2° ext{C} for exactly 30 minutes.
- Washing Phase:
- Gently aspirate serum from wells using a vacuum manifold or discard via rapid flick into disinfectant.
- Immediately submerge slides in a slide-staining jar containing freshly prepared PBS (pH 7.4).
- Agitate gently on a shaker for 5 minutes. Repeat with a second wash in fresh PBS for 5 minutes. Inadequate washing causes persistent background halo fluorescence.
- Secondary Conjugate Incubation:
- Remove slides one by one, blot excess liquid around wells using lint-free gauze, and immediately apply 25 ext{ }mu ext{L} of FITC-conjugate with Evans Blue to each well.
- Incubate in a light-protected humidified chamber for 30 minutes at 22° ext{C}.
- Final Wash and Mounting:
- Repeat the two 5-minute PBS washes in darkness.
- Dip slide briefly (2 seconds) in deionized water to prevent salt crystals from forming upon drying.
- Apply 3 continuous drops of anti-fade mounting medium along the center line.
- Carefully lay a 24 imes 60 ext{ mm} No. 1.5 optical cover slip, avoiding bubble formation.
- Microscopic Evaluation:
- Read immediately under a calibrated epifluorescence microscope using a 40 imes objective (NA ≥ 0.75).
- If using automated digital slide scanners (e.g., EUROPattern, NOVA View, Helios), verify camera exposure times and run internal dark-field calibration.
7. The Two-Tier Reflex Testing Algorithm (Best-Practice Clinical Diagnostic SOP) #
To reconcile the superior screening sensitivity of HEp-2 IFA with the rapid quantitative workflow of multiplex bead technology, leading diagnostic hospitals enforce a two-tier reflex screening algorithm:
                  Two-Tier Autoimmune Diagnostic Reflex Algorithm:
                                  [Patient Serum]
                                         │
                                         ▼
                            HEp-2 Cell IFA Screen (1:160)
                                         │
                      ┌──────────────────┴──────────────────┐
                      ▼                                     ▼
               IFA Negative (<1:160)                 IFA Positive (≥1:160)
                      │                                     │
                      │                        Identify ICAP Pattern (e.g., AC-1)
                      │                                     │
       ┌──────────────┴──────────────┐                      ▼
       ▼                             ▼             Perform Reflex Multiplex Bead Panel
  High Suspicion               SARD Unlikely      (dsDNA, Sm, Ro60, Ro52, SSB, Scl70, RNP)
  for Sjögren's / Lupus?             │                      │
       │                        Report Negative             ▼
       ▼                                           Quantitate Specific Autoantibodies
Run Isolated Ro52 / Ribosomal P                    & Correlate with Clinical Symptoms
Solid-Phase ELISA
7.1 Interpreting Discordant Results #
- Scenario A: IFA Positive (≥ 1:640, Nucleolar AC-8) but Multiplex Bead Array All Negative:
- Interpretation: True autoimmune reactivity. Patient likely has Systemic Sclerosis or Myositis with anti-PM-Scl, Th/To, or RNA Pol I autoantibodies not present on the limited multiplex bead menu. Do not dismiss as false positive.
- Scenario B: IFA Negative (<1:80) but Multiplex Bead Positive for anti-Ro52/SSA (>100 ext{ U/mL}):
- Interpretation: True autoantibody detection. Ro52 (TRIM21) is notoriously prone to denaturation during standard methanol/acetone HEp-2 fixation, yielding false-negative IFA results in up to 20% of anti-Ro52 positive Sjögren's patients. The solid-phase result takes diagnostic precedence.
- Scenario C: IFA Positive (1:640, Dense Fine Speckled AC-2) and Multiplex Screen Weak Positive:
- Interpretation: Perform specific anti-DFS70 testing. If anti-DFS70 is confirmed positive in isolation without other ENA antibodies, the probability of systemic autoimmune disease is <2%.
8. Quality Control, Proficiency Testing, and Validation Metrics #
Clinical laboratories operating under ISO 15189:2022 or CAP (College of American Pathologists) checklist requirements must record the following metrics:
- Endpoint Titer Verification: Every new lot of HEp-2 slides must demonstrate an endpoint titer agreement within ± 1 doubling dilution (e.g., ext{ nominal } 1:640 ext{ must read between } 1:320 ext{ and } 1:1280) using a secondary international reference standard (WHO / CDC ANA Reference Standards).
- Mitotic Cell Verification: A minimum of 2 clearly identifiable mitotic metaphase cells must be visible in every microscopic field of view at 40 imes. Slides lacking mitotic cells must be rejected due to defective cell culture fixation.
- Photobleaching Prevention: Modern anti-fade agents containing DABCO must preserve ≥ 80% of initial fluorescent intensity over a minimum observation window of 120 seconds under direct blue excitation.
9. Comprehensive Troubleshooting Matrix #
| Problem | Potential Root Cause | Diagnostic Confirmation | Resolution / Corrective Action |
|---|---|---|---|
| All slides show intense green non-specific background | Substrate dried out during manual primary or secondary incubation | Cells exhibit edge-halo drying artifacts under brightfield | Keep incubation chamber strictly humidified; do not process more than 4 slides at a time during manual blotting |
| Complete absence of fluorescence in all wells (including controls) | Dichroic filter block misaligned or LED excitation channel set incorrectly | Inspect excitation light with white card in specimen plane | Switch filter set to FITC (495/520 ext{ nm}); check light source power supply and software shutter activation |
| Controls pass, but metaphase chromosomes in positive cells are pitch black | Patient possesses non-chromatin speckled autoantibodies (e.g., anti-Sm/RNP, AC-4/AC-5) | Chromatin plate in dividing cells is dark against green interphase nucleoplasm | Expected true result for anti-ENA antibodies; document as speckled pattern with negative mitotic chromatin |
| High false-positive rate in healthy population (titers 1:160) | Primary screening dilution set too low for adult demographic | Run CDC healthy control cohort (N=100) | Shift clinical screening cutoff from 1:80 to 1:160; incorporate reflex testing for anti-DFS70 |
| Automated digital reader fails to focus on wells | Evans Blue counterstain concentration incorrect or missing | Red cytoplasmic baseline signal is absent | Use validated conjugate containing 0.005% ext{ Evans Blue}; clean slide bottom surface with 70% ext{ isopropanol} |
10. References and International Consensus Guidelines #
- Damoiseaux, J., et al. (2019). Clinical evaluation of the International Consensus on ANA Patterns (ICAP) in an international multi-center study. The Journal of Applied Laboratory Medicine, 4(4), 652–660.
- Agmon-Levin, N., et al. (2014). International recommendations for the assessment of autoantibodies to cellular antigens referred to as anti-nuclear antibodies. Annals of the Rheumatic Diseases, 73(1), 17–23.
- Bossuyt, X., et al. (2020). Detection of antinuclear antibodies: recommendations from EASI and ICAP. Nature Reviews Rheumatology, 16(11), 643–654.
- Mahler, M., & Fritzler, M. J. (2012). The clinical significance of the dense fine speckled immunofluorescence pattern on HEp-2 cells for the diagnosis of systemic autoimmune diseases. Clinical and Developmental Immunology, vol. 2012, Article ID 494356.
- ISO 15189:2022. Medical laboratories — Requirements for quality and competence. International Organization for Standardization.