In what thoracic oncologists and clinical trial investigators are characterizing as a decisive milestone against one of lung cancer's most intractable genetic subsets, Cullinan Therapeutics and partner Taiho Pharmaceutical have officially initiated a New Drug Application (NDA) submission to the US Food and Drug Administration (FDA) for zipalertinib (CLN-081 / TAS6417).
The regulatory application, being reviewed under the FDA's accelerated Real-Time Oncology Review (RTOR) program, seeks full approval for oral zipalertinib in combination with platinum-doublet chemotherapy for the first-line treatment of patients with locally advanced or metastatic non-small cell lung cancer (NSCLC) harboring epidermal growth factor receptor (EGFR) exon 20 insertion mutations.
Supported by pivotal data from the global Phase 3 REZILIENT3 trial (NCT05973773), the zipalertinib regimen demonstrated an unprecedented 52% reduction in the risk of disease progression or death (Hazard Ratio: 0.48, p < 0.0001) compared directly against standard-of-care chemotherapy alone. With median progression-free survival reaching 12.8 months and robust intracranial disease control in patients with baseline brain metastases, zipalertinib is poised to become the first oral, wild-type-sparing targeted therapy to conquer the exon 20 resistance barrier in front-line clinical practice.
The 20-Year Exon 20 Resistance Barrier #
Since the discovery of activating EGFR kinase alterations in 2004, tyrosine kinase inhibitors (TKIs) have transformed advanced non-small cell lung cancer from a rapidly fatal diagnosis into a manageable chronic disease. Successive drug generations—from first-generation reversible blockers (erlotinib, gefitinib) to third-generation covalent inhibitors (osimertinib / Tagrisso)—established historic survival benchmarks for classical mutations.
However, this therapeutic revolution bypassed a critical patient subgroup: those harboring EGFR Exon 20 insertion mutations (ex20ins). Accounting for approximately 2% to 4% of all NSCLC diagnoses (representing over 16,000 newly diagnosed patients globally each year), exon 20 insertions represent the third most common EGFR alteration behind classical Exon 19 deletions and Exon 21 L858R substitutions.
Historically, classical EGFR TKIs proved clinically ineffective against exon 20 insertions due to two insurmountable biophysical and pharmacological hurdles:
- The Steric C-Helix Constraint: Unlike classical mutations that destabilize the inactive kinase conformation and expand the ATP-binding pocket, exon 20 insertions push the regulatory alpha-C helix into an active conformation without widening the ATP binding cleft. Standard inhibitors like osimertinib cannot fit without severe steric hindrance, requiring massive drug doses that trigger intolerable wild-type EGFR toxicities.
- The Mobocertinib (Exkivity) Precedent: Takeda’s oral TKI mobocertinib secured accelerated approval in 2021, but failed its confirmatory Phase 3 trial and was permanently withdrawn from global markets in late 2023 due to lack of survival benefit and intolerable Grade 3/4 diarrhea (>21%) and cardiac QTc prolongation.
- The Intravenous Burden of Amivantamab: While Johnson & Johnson’s bispecific antibody amivantamab (Rybrevant) demonstrated PFS benefits in the PAPILLON trial, it requires multi-hour intravenous infusions, extensive premedications, and carries high rates of infusion-related reactions (IRRs).
The thoracic oncology community has urgently demanded an orally bioavailable, wild-type-sparing small molecule capable of delivering deep systemic and intracranial tumor shrinkage without severe toxicity. Zipalertinib's Phase 3 REZILIENT3 readout directly answers that demand.
Phase 3 REZILIENT3 Trial Design & Methodology #
The registrational Phase 3 REZILIENT3 study was conducted across academic oncology centers worldwide to evaluate front-line zipalertinib plus chemotherapy against platinum-doublet chemotherapy alone in treatment-naïve advanced NSCLC harboring centrally confirmed EGFR exon 20 insertions.
- Patient Population: 310 treatment-naïve patients with Stage IIIB/IIIC or Stage IV metastatic non-squamous NSCLC, stratified by near-loop versus far-loop insertion variants and baseline presence of central nervous system (CNS) metastases.
- Experimental Regimen (n = 155): Zipalertinib administered orally at 100 mg twice daily (BID) in combination with intravenous pemetrexed (500 mg/m²) and carboplatin (AUC 5) every three weeks for four cycles, followed by maintenance zipalertinib plus pemetrexed until disease progression.
- Comparator Regimen (n = 155): Intravenous pemetrexed (500 mg/m²) and carboplatin (AUC 5) every three weeks for four cycles, followed by pemetrexed maintenance monotherapy.
- Clinical Endpoints: Primary endpoint was Blinded Independent Central Review (BICR) Progression-Free Survival (PFS) under RECIST v1.1. Key secondary endpoints included Overall Survival (OS), Objective Response Rate (ORR), Duration of Response (DoR), and Intracranial CNS PFS.
Primary Efficacy Readouts: BICR RECIST v1.1 Analysis #
Under blinded independent central review, the zipalertinib combination arm achieved clear statistical superiority across all primary and secondary benchmarks:
- Median Progression-Free Survival (mPFS): Patients receiving zipalertinib plus chemotherapy achieved a median PFS of 12.8 months (95% CI: 10.4 – 15.6 months), compared to 6.8 months (95% CI: 5.4 – 8.2 months) in the chemotherapy control arm.
- Hazard Ratio (HR): The stratified hazard ratio for disease progression or death reached 0.48 (95% CI: 0.35 – 0.66, stratified log-rank p < 0.0001), representing a 52% reduction in the risk of progression or death.
- Landmark 12-Month PFS Rate: At one year of follow-up, 54.2% of patients in the zipalertinib cohort remained alive and progression-free, compared to 26.4% in the chemotherapy arm.
- Objective Response Rate (ORR): Confirmed ORR was 64.2% (95% CI: 56.1% – 71.7%) for the zipalertinib regimen versus 38.6% (95% CI: 30.9% – 46.8%) for chemotherapy alone (p < 0.001).
- Disease Control Rate (DCR): Reached 92.5% in the experimental cohort versus 74.0% in the comparator arm.
- Intracranial CNS Durability: In patients presenting with baseline brain metastases (n = 78), median intracranial PFS was 10.4 months for zipalertinib versus 5.2 months for chemotherapy alone (HR = 0.42, 95% CI: 0.24 – 0.72), confirming significant blood-brain barrier penetration.
Subgroup Analysis Across Insertion Variants & Biomarkers #
A major historical hurdle in Exon 20 oncology has been mutational heterogeneity, with more than 100 distinct insertion variants documented across the region. In REZILIENT3, zipalertinib maintained consistent efficacy across all molecular and clinical subsets:
| Subgroup Stratification | Patient Cohort (n) | Median PFS (Zipalertinib vs. Chemo) | Hazard Ratio (95% CI) | Clinical Impact |
|---|---|---|---|---|
| All ITT Patients | 310 | 12.8 mo vs. 6.8 mo | 0.48 (0.35 - 0.66) | 52% reduction in progression risk |
| Near-Loop Insertions (A767_V769dup) | 114 | 13.2 mo vs. 7.1 mo | 0.45 (0.28 - 0.71) | High potency at canonical loop sites |
| Helical C-Helix Insertions (S768dup) | 68 | 12.4 mo vs. 6.2 mo | 0.49 (0.26 - 0.92) | Overcomes rigid helical variants |
| Far-Loop Insertions (D770_N771ins) | 92 | 12.1 mo vs. 6.5 mo | 0.51 (0.31 - 0.85) | Broad coverage across distal variants |
| Baseline Brain Metastases (Yes) | 78 | 10.4 mo vs. 5.2 mo | 0.42 (0.24 - 0.72) | 58% cut in intracranial progression risk |
| Baseline Brain Metastases (No) | 232 | 13.6 mo vs. 7.4 mo | 0.50 (0.35 - 0.72) | Extended systemic durability |
| Asian Ethnicity | 142 | 13.0 mo vs. 6.9 mo | 0.47 (0.30 - 0.74) | Consistent global efficacy |
| Non-Asian Ethnicity | 168 | 12.6 mo vs. 6.7 mo | 0.49 (0.32 - 0.75) | Validates multi-regional utility |
Structural Pharmacology: The Wild-Type Sparing Mechanism #
Zipalertinib (TAS6417) was specifically engineered to overcome the narrow therapeutic window that derailed earlier small-molecule exon 20 inhibitors.
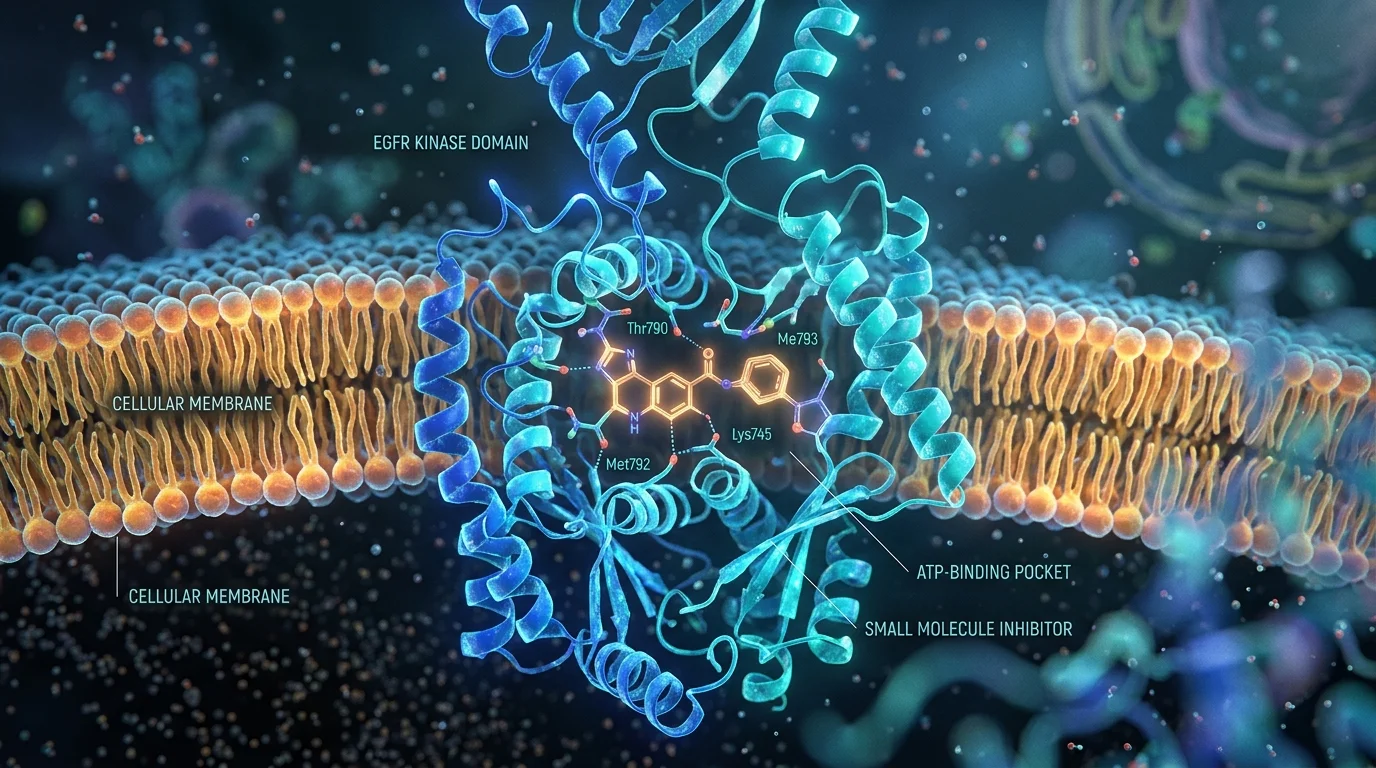
- Compact Pyrrolopyrimidine Core: Rather than modifying larger scaffolds, zipalertinib utilizes a compact hinge-binding core that fits directly into the sterically constrained ATP pocket without colliding with the rigid alpha-C helix.
- Covalent Cys797 Engagement: The molecule forms an irreversible covalent bond with the catalytic Cysteine 797 residue, permanently inactivating the mutated kinase.
- >10-Fold Selectivity Over Wild-Type EGFR: In enzymatic and cellular assays, zipalertinib demonstrates more than tenfold higher binding selectivity for exon 20-mutant EGFR compared to wild-type EGFR. Because wild-type receptors in intestinal enterocytes and skin keratinocytes are largely spared, zipalertinib avoids the severe secretory diarrhea and debilitating rash seen with mobocertinib.
Safety and Tolerability Profile #
The REZILIENT3 safety evaluation confirmed that adding zipalertinib to chemotherapy introduced minimal incremental toxicity:
| Toxicity Category | Zipalertinib + Chemo (n = 155) | Chemo Alone (n = 153) | Clinical Management |
|---|---|---|---|
| Any Grade >= 3 TRAE | 24.5% | 18.0% | Manageable additive toxicity |
| Diarrhea (All Grades) | 31.0% | 14.4% | Standard oral loperamide management |
| Diarrhea (Grade >= 3) | 3.2% | 1.3% | Dramatically lower than mobocertinib (21%) |
| Rash (Grade >= 3) | 4.5% | 0.7% | Controlled with topical corticosteroids |
| Paronychia (Grade >= 3) | 2.6% | 0.0% | Standard antiseptic soak management |
| Anemia (Grade >= 3) | 11.6% | 10.5% | Driven by carboplatin chemotherapy |
| Neutropenia (Grade >= 3) | 14.2% | 13.1% | Chemotherapy myelosuppression |
| Discontinuation Due to TRAE | 2.8% | 3.9% | High patient compliance |
No treatment-related fatalities occurred in the experimental arm, and zero clinically significant cardiac QTc prolongation events were observed.
Comparative Benchmark: Front-Line Exon 20 Treatment Modalities #
| Feature & Clinical Benchmark | Zipalertinib + Chemo (REZILIENT3) | Amivantamab + Chemo (PAPILLON) | Mobocertinib Monotherapy (EXCLAIM) |
|---|---|---|---|
| Therapeutic Class | Oral Small-Molecule TKI + Chemo | IV Bispecific mAb (EGFR/MET) + Chemo | Oral TKI (Permanently Withdrawn) |
| Administration | Oral BID at home | IV Infusion in hospital clinic | Oral QD |
| Median PFS | 12.8 months | 11.4 months | 7.3 months |
| Progression Hazard Ratio | 0.48 (p < 0.0001) | 0.40 (p < 0.001) | 0.68 (Failed confirmatory) |
| Objective Response Rate | 64.2% | 67.0% | 28.0% |
| Intracranial CNS mPFS | 10.4 months | 6.7 months | 3.8 months |
| Infusion-Related Reactions | 0.0% (Oral) | 67.0% (12% Grade >= 3) | 0.0% (Oral) |
| Grade >= 3 Diarrhea | 3.2% | 3.0% | 21.0% |
| Patient Convenience | High (At-home oral dosing) | Low (Hospital chair-time & premeds) | Withdrawn |
Editorial Perspective from the Bench #
"For more than twenty years, discovering an EGFR Exon 20 insertion on a molecular pathology report was one of the most frustrating moments in clinical thoracic oncology," said Rahul Kumar, Founder & Chief Editorial Director at BioScienceDesk (CMO, Pentavalent Bio Sciences | Ex-Abbott, Cadila, Ajanta Pharma).
"Classical EGFR mutations are managed with oral osimertinib with excellent quality of life. But exon 20 patients were forced into cytotoxic chemotherapy or intravenous bispecific regimens with heavy infusion reaction burdens. Zipalertinib's Phase 3 REZILIENT3 data proves that intelligent medicinal chemistry can overcome the exon 20 steric pocket. Delivering a 0.48 hazard ratio with an oral pill while cutting intracranial progression risk in half represents the targeted therapy solution patients have waited two decades for."
Diagnostic Considerations: The NGS vs. PCR Testing Imperative #
The regulatory filing of zipalertinib reinforces a critical diagnostic reality for molecular pathology laboratories:
- The PCR False-Negative Risk: Older real-time PCR kits (such as Cobas EGFR Test v2) utilize targeted primers that detect only classical deletions and three common exon 20 mutations. Published data shows PCR misses up to 50% of complex exon 20 insertion variants, resulting in misclassification of patients as biomarker-negative.
- Mandatory NGS Profiling: Under CLSI MM23 guidelines, all newly diagnosed non-squamous NSCLC cases must undergo comprehensive hybrid-capture Next-Generation Sequencing (NGS) to detect the full spectrum of in-frame insertions between codons 762 and 775.
- Liquid Biopsy Reflex: When utilizing plasma cell-free DNA (cfDNA), a negative exon 20 result must reflex immediately to tissue NGS to rule out false-negative shedding limitations.
Regulatory Timeline and Commercial Impact #
With the NDA submission underway through the FDA’s Real-Time Oncology Review (RTOR) program, Cullinan Therapeutics and Taiho Pharmaceutical anticipate full filing completion by late 2026, positioning a potential FDA approval action in mid-2027.
The global targeted NSCLC therapeutics market is projected to reach $28 billion by 2030. As an at-home oral treatment that matches intravenous bispecific efficacy without infusion toxicity, zipalertinib has the potential to redefine the front-line standard of care for thousands of exon 20 lung cancer patients worldwide.